
"Translating Regeneration into Life"
Document Type : Case Reports
Authors
1 Department of Burn Surgery, Faculty of Medicine, Mazandaran University of Medical Sciences, Sari, Iran.
2 School of Medicine, North Khorasan University of Medical Sciences, Bojnurd, Iran.
3 Department of Anesthesiology, Faculty of Medicine, Mazandaran University of Medical Sciences, Sari, Iran.
4 Faculty of Medicine, Mazandaran University of Medical Sciences, Sari, Iran.
Keywords
Introduction
Lithium-ion batteries are widely used in portable electronics. When internal failure causes thermal runaway, rapid heat release, flame, hot fragments, and electrolyte leakage may produce combined thermal, chemical, and blast injury. Contemporary burn center series indicate that presentations related to lithium-ion devices are increasing and range from limited superficial injury to deep burns requiring excision and grafting [1-4]. Thermal injury can cause protein denaturation and coagulative necrosis, whereas alkaline or reactive electrolyte components can penetrate tissue and extend damage after the initial event. Consequently, burn depth may evolve, and serial examination is important [2, 5, 6]. Facial and periorbital injuries additionally require early airway and ophthalmologic assessment because edema and ocular exposure can threaten function.
Human amniotic membrane (hAM) is an avascular placental tissue composed of an epithelial layer, basement membrane, and stromal matrix. It has low immunogenicity and contains extracellular matrix components and signaling molecules associated with epithelial migration and inflammation control [7, 8]. Clinical studies and evidence syntheses in burn care have reported shorter healing time, fewer dressing changes, and reduced pain in selected partial-thickness wounds, although study quality, products, and processing methods vary [9-12]. This case report describes the use of hAM for a case with a facial chemo-thermal burn after a smartphone battery explosion. As a biologic dressing, hAM is thin, flexible, conformable to an irregular wound surface, semipermeable, and relatively low in immunogenicity; its collagen-rich basement membrane and stromal matrix can provide a protective scaffold that supports epithelial migration and a moist wound environment [7, 8, 13].
Case Presentation
The case was a 17-year-old female with no known previous medical condition who presented after a newly released branded smartphone exploded while being used during charging. Burns involved the face, anterior neck, and both hands, predominantly the right hand. Marked facial and periorbital edema was present on admission, and the patient was monitored in the intensive care unit for 48 hours. After edema subsided, examination showed superficial partial-thickness (superficial second-degree) burns involving approximately 8% of total body surface area (Figure 1).
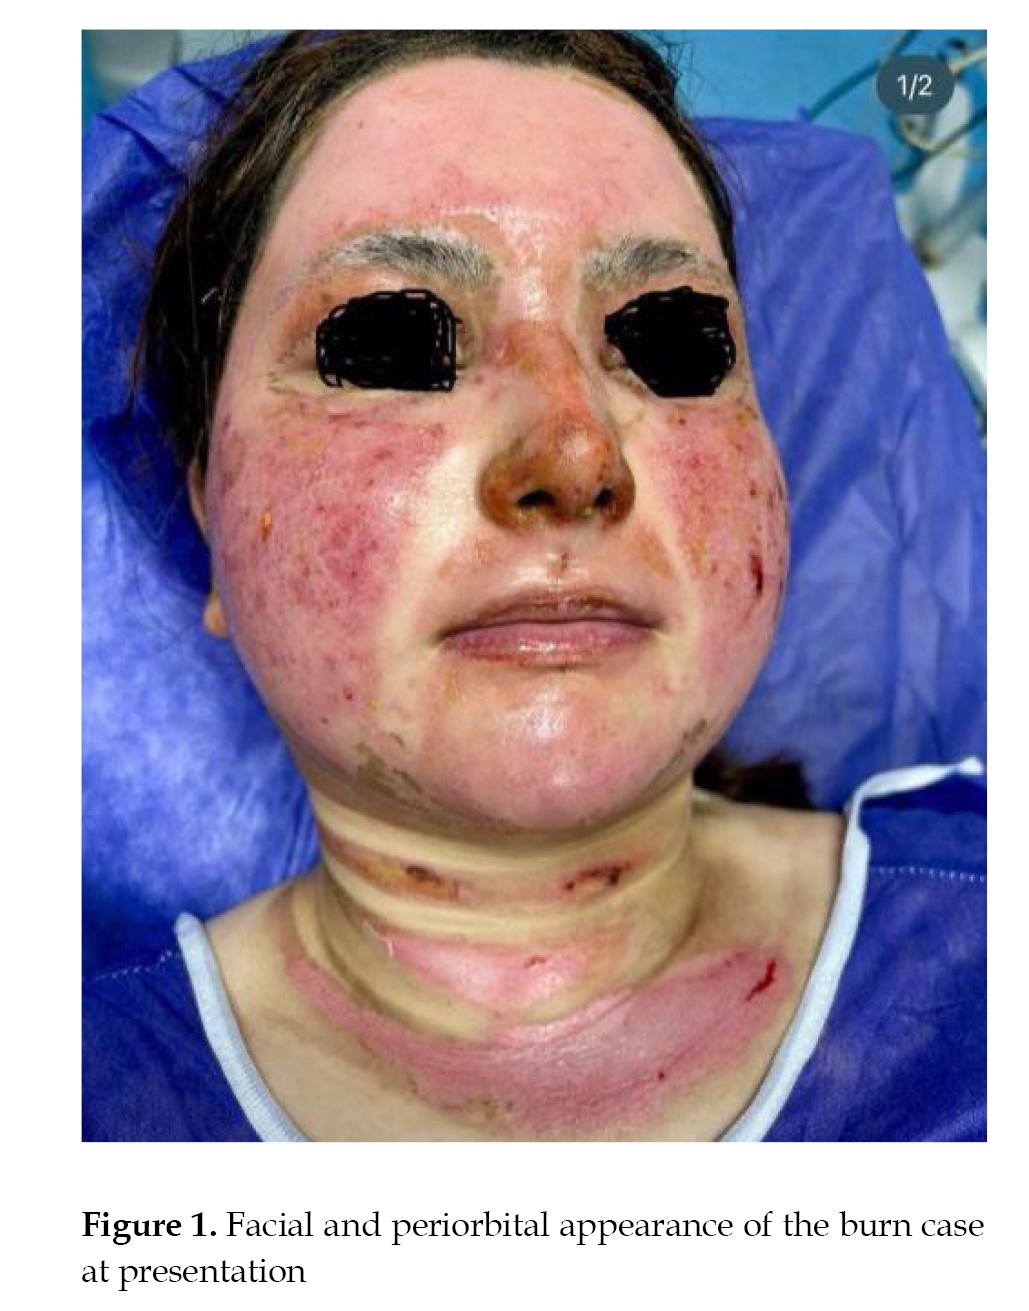
The wounds were erythematous and painful without documented blistering. Ophthalmologic assessment was normal.
During the first two days, mupirocin ointment and a conventional dressing were used. After two days of topical mupirocin, reduction of facial edema, and reassessment of burn depth, a hAM dressing with the required size was opened using aseptic technique and applied to the cleansed wound surface. We used ready-to-use, presterilized hAM dressings manufactured by AmiCare as temporary biologic wound coverings. The product is derived from human placental amnion and is processed and sterilized by the manufacturer before distribution. It is supplied in sealed sterile packaging and in dimensions selected to match the wound area. Manufacturer processing and terminal-sterilization parameters were not repeated at the treating center. It was covered with a sterile non-adherent secondary dressing and monitored clinically while epithelialization progressed. Near-complete healing was documented five days later. By day 5 post-hAM placement, the wounds were almost completely epithelialized, with mild residual erythema (Figure 2).
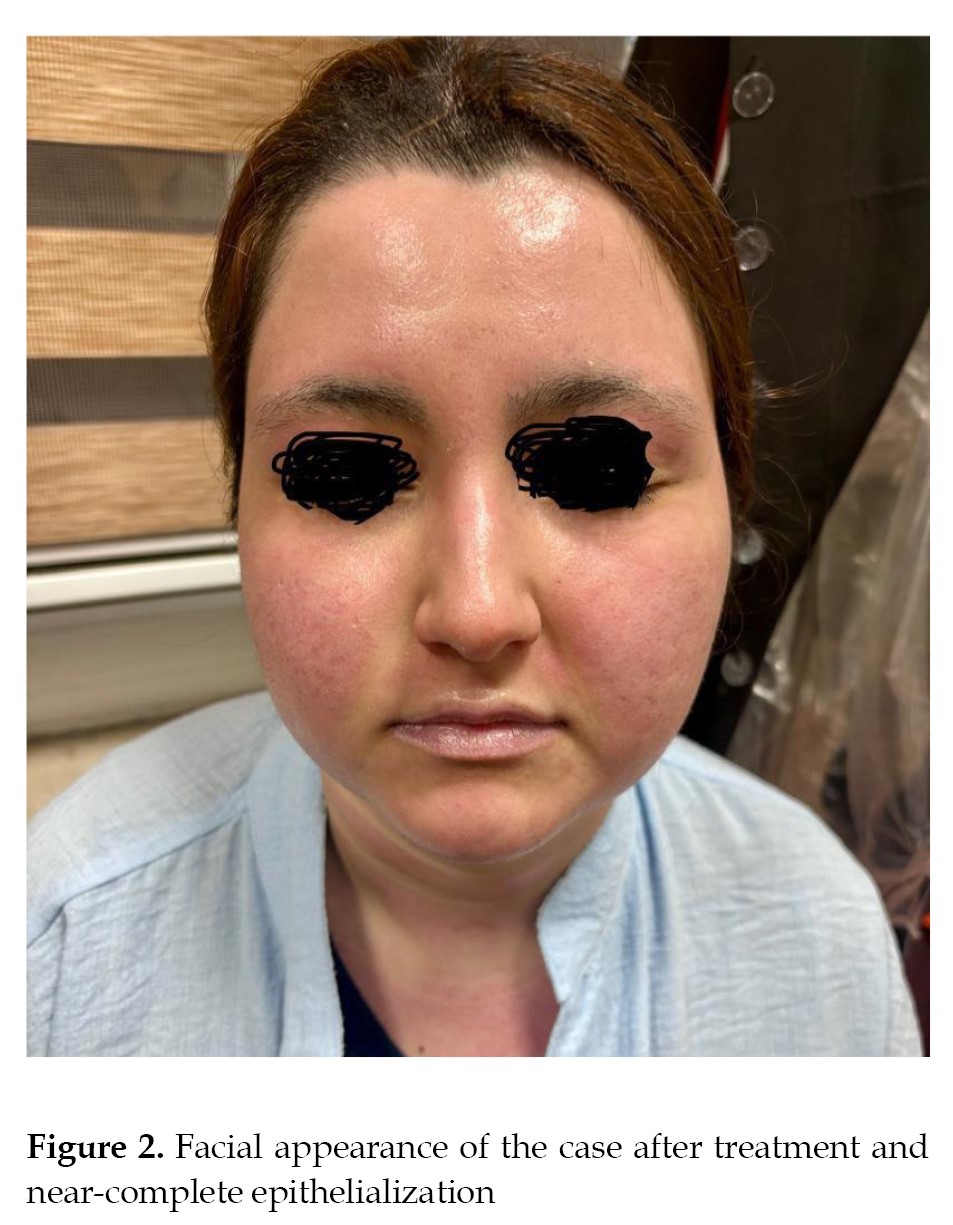
The patient reported no pain at that time and was satisfied with facial appearance. No ocular or functional complication was documented.
Discussion
This study reported a rare but anatomically critical facial, neck, and hand burn case following smartphone-battery explosion. Rapid recovery was observed following initial topical antimicrobial care and subsequent hAM coverage. This observation is clinically relevant because lithium-ion battery injuries may combine thermal runaway, hot debris, and electrolyte exposure, and because facial burns prioritize tissue preservation and cosmetic outcome [1-4].
Published battery-related burn reports mainly describe irrigation, topical therapy, debridement, and, for deep injury, excision and split-thickness grafting. In our study, we managed a mobile phone explosion-induced burn with enzymatic debridement, whereas studies of larger-device and wearable-battery cases included full-thickness injury and operative treatment [2-4]. Direct comparison with these studies was not possible because of differences in device type, exposure, burn depth, and anatomic sites.
The biologic rationale for hAM includes a basement-membrane scaffold, low immunogenicity, and anti-inflammatory and antifibrotic signaling. Processing methods are not interchangeable and may alter cellular viability, matrix structure, mechanical behavior, or growth-factor retention [7, 8, 13]. In this study, a commercially prepared, presterilized AmiCare hAM product was used; its processing and sterilization had been done by the manufacturer, not by the clinical team.
Evidence for hAM in cutaneous burns is encouraging but heterogeneous. A 2021 meta-analysis of 11 randomized clinical trials (RCTs) found benefits over several conventional comparators but emphasized the need for stronger trials [9]. An RCT comparing hAM with nitrofurazone-impregnated gauze reported faster epithelialization, lower pain, fewer dressing changes, and less early scarring [10]. A 2024 RCT comparing hAM with silver sulfadiazine similarly reported earlier epithelialization and lower pain, although its open-label design and specific lyophilized, irradiated product limit generalization [11]. A contemporary RCT protocol further illustrated the field’s move toward standardized, traceable, in-hospital tissue-bank products [12].
The five-day clinical course in our patient is consistent with rapid healing of a superficial partial-thickness burn, and hAM may have supported a moist, protected wound environment. However, causation cannot be shown because there was no comparator, objective pain series, blinded wound assessment, or standardized scar follow-up. This report is therefore limited to feasibility and temporal association rather than treatment superiority.
This is a single case study with no control treatment. Burn depth was clinically assessed, and the source record did not include a validated serial pain score, objective epithelialized-area measurement, standardized scar scale, or long-term follow-up. The hAM dressing was ready to use and sterile; the treating team did not independently evaluate proprietary processing and terminal-sterilization parameters. The conclusion is therefore hypothesis-generating.
Conclusion
The hAM use was feasible as a temporary biologic dressing in a female adolescent with a superficial partial-thickness facial chemo-thermal burn caused by smartphone-battery explosion, with near-complete epithelialization observed within five days. The favorable course supports further prospective evaluation using traceable, standardized hAM products and longer scar and functional follow-up.
Ethical Considerations
Compliance with ethical guidelines
Under the policy of the treating institution, a single-patient case report does not require research ethics committee review or an ethics approval number. The report was prepared in accordance with applicable institutional requirements and the principles of the Declaration of Helsinki.
Funding
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for profit sectors.
Authors' contributions
Conceptualization, clinical care, and supervision: Mehdi Hojjati; Data collection and investigation: Amirsaleh Abdollahi; Investigation and writing the original draft: Sajjad Toofani; Supervision, and project administration, review and editing: Samira Sobhani; Final approval: All authors.
Conflict of interest
The authors declared no conflict of interest.
Acknowledgments
The authors would like to express their sincere gratitude to the Department of Anesthesiology and the Burn Department of Mazandaran University of Medical Sciences for their valuable support, cooperation, and assistance throughout the course of this study. We also extend our appreciation to all faculty members, clinical staff, and personnel whose contributions facilitated the successful completion of this work.
References
1. Duff M, Manzanero S, Barker R, Barlas P, Westacott G, Lisec C. Lithium-ion battery related burns and emerging trends: a retrospective case series and data analysis of emergency presentations. ANZ Journal of Surgery. 2024; 94(11):1983-9. [DOI:10.1111/ans.19218] [PMID]
2. Cherubino M, Pellegatta I, Sallam D, Pulerà E, Valdatta L. Enzymatic debridement after mobile phone explosion: A case report. Annals of Burns and Fire Disasters. 2016; 29(4):273-5. [PMID]
3. Diab J, O’Hara J, Fisher AI, La Hei E, Gates R, Vandervord J, et al. Exploding power: A statewide review of lithium battery related burns. Australasian Journal of Plastic Surgery. 2021; 4(2). [DOI:10.34239/ajops.v4n2.247]
4. Cole-Price AK, Silverman E, Sienko P, Molvik H, Vercruysse GA. An initial report of thermal runaway resulting in full-thickness foot burns from lithium-ion battery-powered insole. Journal of Burn Care & Research. 2024; 45(6):1636-40. [DOI:10.1093/jbcr/irae157] [PMID]
5. Szymanski KD, Tannan SC. Thermal Burns. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan. [PMID]
6. Akelma H, Karahan ZA. Rare chemical burns: Review of the literature. International Wound Journal. 2019; 16(6):1330-8. [DOI:10.1111/iwj.13193] [PMID]
7. Hofmann N, Rennekampff HO, Salz AK, Börgel M. Preparation of human amniotic membrane for transplantation in different application areas. Frontiers in Transplantation. 2023; 2:1152068. [DOI:10.3389/frtra.2023.1152068] [PMID]
8. Ingraldi AL, Audet RG, Tabor AJ. The preparation and clinical efficacy of amnion-derived membranes: A review. Journal of Functional Biomaterials. 2023; 14(10):531. [DOI:10.3390/jfb14100531] [PMID]
9. Yang C, Xiong AB, He XC, Ding XB, Tian XL, Li Y, et al. Efficacy and feasibility of amniotic membrane for the treatment of burn wounds: Ameta-analysis. The journal of Trauma and Acute Care Surgery. 2021; 90(4):744-55. [DOI:10.1097/TA.0000000000003050] [PMID]
10. Kazemzadeh J, Yousefiazar A, Zahedi A. Amniotic membrane dressing versus nitrofurazone-impregnated dressing in the treatment of second-degree burn wounds: A randomized clinical trial. Wounds. 2022; 34(1):11-16. [DOI:10.25270/wnds/082421.04] [PMID]
11. Moghimi MH, Salehian M, Abdi M, Tahrekhani M, Safaei A, Kamali K. The impact of an open-label design on human amniotic membranes vs. silver sulfadiazine dressings for second-degree burns: A randomized controlled clinical trial. BMC Surgery. 2024; 24(1):309. [DOI:10.1186/s12893-024-02554-5] [PMID]
12. Pfister P, Wendel-Garcia PD, Meneau I, Vasella M, Watson JA, Bühler P, et al. Human amniotic membranes as an allogenic biological dressing for the treatment of burn wounds: Protocol for a randomized-controlled study. Contemporary Clinical Trials Communications. 2023; 36:101209.[DOI:10.1016/j.conctc.2023.101209] [PMID]
13. Leal-Marin S, Kern T, Hofmann N, Pogozhykh O, Framme C, Börgel M, et al. Human amniotic membrane: a review on tissue engineering, application, and storage. Journal of Biomedical Materials Research. Part B, Applied Biomaterials. 2021; 109(8):1198-215. [DOI:10.1002/jbm.b.34782] [PMID]
14. Hatzfeld AS, Pasquesoone L, Germain N, Danzé PM, Drucbert AS, Tardivel M, et al. Benefits of cryopreserved human amniotic membranes in association with conventional treatments in the management of full-thickness burns. International Wound Journal. 2019; 16(6):1354-64. [DOI:10.1111/iwj.13198] [PMID]
15. Eskandarlou M, Azimi M, Rabiee S, Seif Rabiee MA. The healing effect of amniotic membrane in burn patients. World Journal of Plastic Surgery. 2016; 5(1):39-44. [PMID]
16. Kesting MR, Wolff KD, Hohlweg-Majert B, Steinstraesser L. The role of allogenic amniotic membrane in burn treatment. Journal of Burn Care & Research. 2008; 29(6):907-16. [DOI:10.1097/BCR.0b013e31818b9e40] [PMID]

